



A lifelong prescription for a problem no one is trying to solve: a root-cause and risk-benefit reckoning
Share the X thread dedicated to this post here.
Imagine your smoke alarm goes off in the middle of the night. You have two choices. You can find the fire. Or you can buy a subscription service that injects a chemical into the alarm once a week so it stops making noise, while the house keeps burning.
For a growing share of the population, the second option is now the standard of care.
Around 12% of U.S. adults are now taking a GLP-1 drug like Ozempic, Wegovy, Mounjaro, or Zepbound (Associated Press, citing KFF). In 2025 alone, Eli Lilly’s tirzepatide franchise brought in about $36.5 billion, outselling Keytruda, the cancer drug long considered the most lucrative product in pharmaceutical history (BioSpace). The leading medical societies now say these drugs, once started, are meant for “long-term or lifelong use” (Obesity, 2026).
Read that again. Lifelong. For a condition that barely existed at population scale two generations ago.
That is the absurdity I want to examine. My argument is not that these drugs do nothing; they clearly change the numbers on the scale and on the lab report. My argument is that they do nothing to address why those numbers went wrong in the first place. And once you see the full ledger of risks against that backdrop, the approach looks less like a medical breakthrough and more like an elaborate, profitable way of not asking the obvious question.
The Old Paradigm in a New Syringe
In REGENERATE, I described what I call the Old Paradigm of metabolic disease:
“In the Old Paradigm, metabolic disorders are treated with a combination of palliative, symptom-reducing drugs and often superficially focused lifestyle and dietary recommendations.”

When I wrote that, the drugs in question were metformin, sulfonylureas, and thiazolidinediones. I noted that people taking metformin, “which doesn’t address the underlying cause,” are often tempted to treat it as a safety net that lets them eat whatever they want. The result, I wrote, is that “a bad diet can lead to questionable medications. It’s a trap that’s snagged millions of Americans.”
GLP-1 agonists are the most sophisticated version of that trap ever built. They don’t repair insulin resistance at its source. They don’t remove the endocrine-disrupting chemicals in our food packaging, restore the microbiome, or fix circadian disruption or chronic stress. What they do is pharmacologically override the body’s appetite and digestive signals: they slow the stomach, blunt hunger in the brain, and force the pancreas’s hand.
The central principle of my work is this: the symptoms of disease are often the body’s intelligent response to something unhealthy or inappropriate. As I put it in the book:
“It is always better to look for the disease’s root cause than to suppress the symptoms.”
And more pointedly:
“Metabolic disease, like virtually all disease, is not so much a force of adversity that accosts us from outside in but our body’s attempt to deal with the onslaught of a radically inappropriate diet, a vast array of toxicant exposures, inactivity, and persistent, health-degrading stress.”
If that is true, and the evidence below suggests it largely is, then a drug that silences the body’s signals while leaving the onslaught intact is not a cure. It is a mute button.
Exhibit A: The Weight Comes Back the Moment You Stop
The clearest proof that a treatment doesn’t touch the root cause is what happens when you stop it. If you put out a fire, it stays out. If you only muffle the alarm, the noise returns the moment the muffling wears off.
That is exactly what the data show.
The evidence: withdrawal trials
STEP 1 extension (semaglutide). Participants lost 17.3% of body weight over 68 weeks. One year after stopping, they had regained two-thirds of it, and “cardiometabolic improvements … reverted towards baseline … for most variables.” The authors, writing in a Novo Nordisk–sponsored trial, concluded the findings “suggest ongoing treatment is required” (Wilding et al., Diabetes, Obesity and Metabolism, 2022).
SURMOUNT-4 (tirzepatide). Participants who were switched to placebo after 36 weeks regained 14% of their body weight over the following year. The authors concluded: “withdrawing tirzepatide led to substantial regain of lost weight” (Aronne et al., JAMA, 2024).
BMJ meta-analysis (37 studies, 9,341 participants). Weight returned at roughly 0.4 kg per month after stopping medication, with a projected return to baseline in about 1.7 years. Blood sugar, blood pressure, and lipids drifted back toward baseline within about 1.4 years (BMJ 2026, via Science Media Centre).
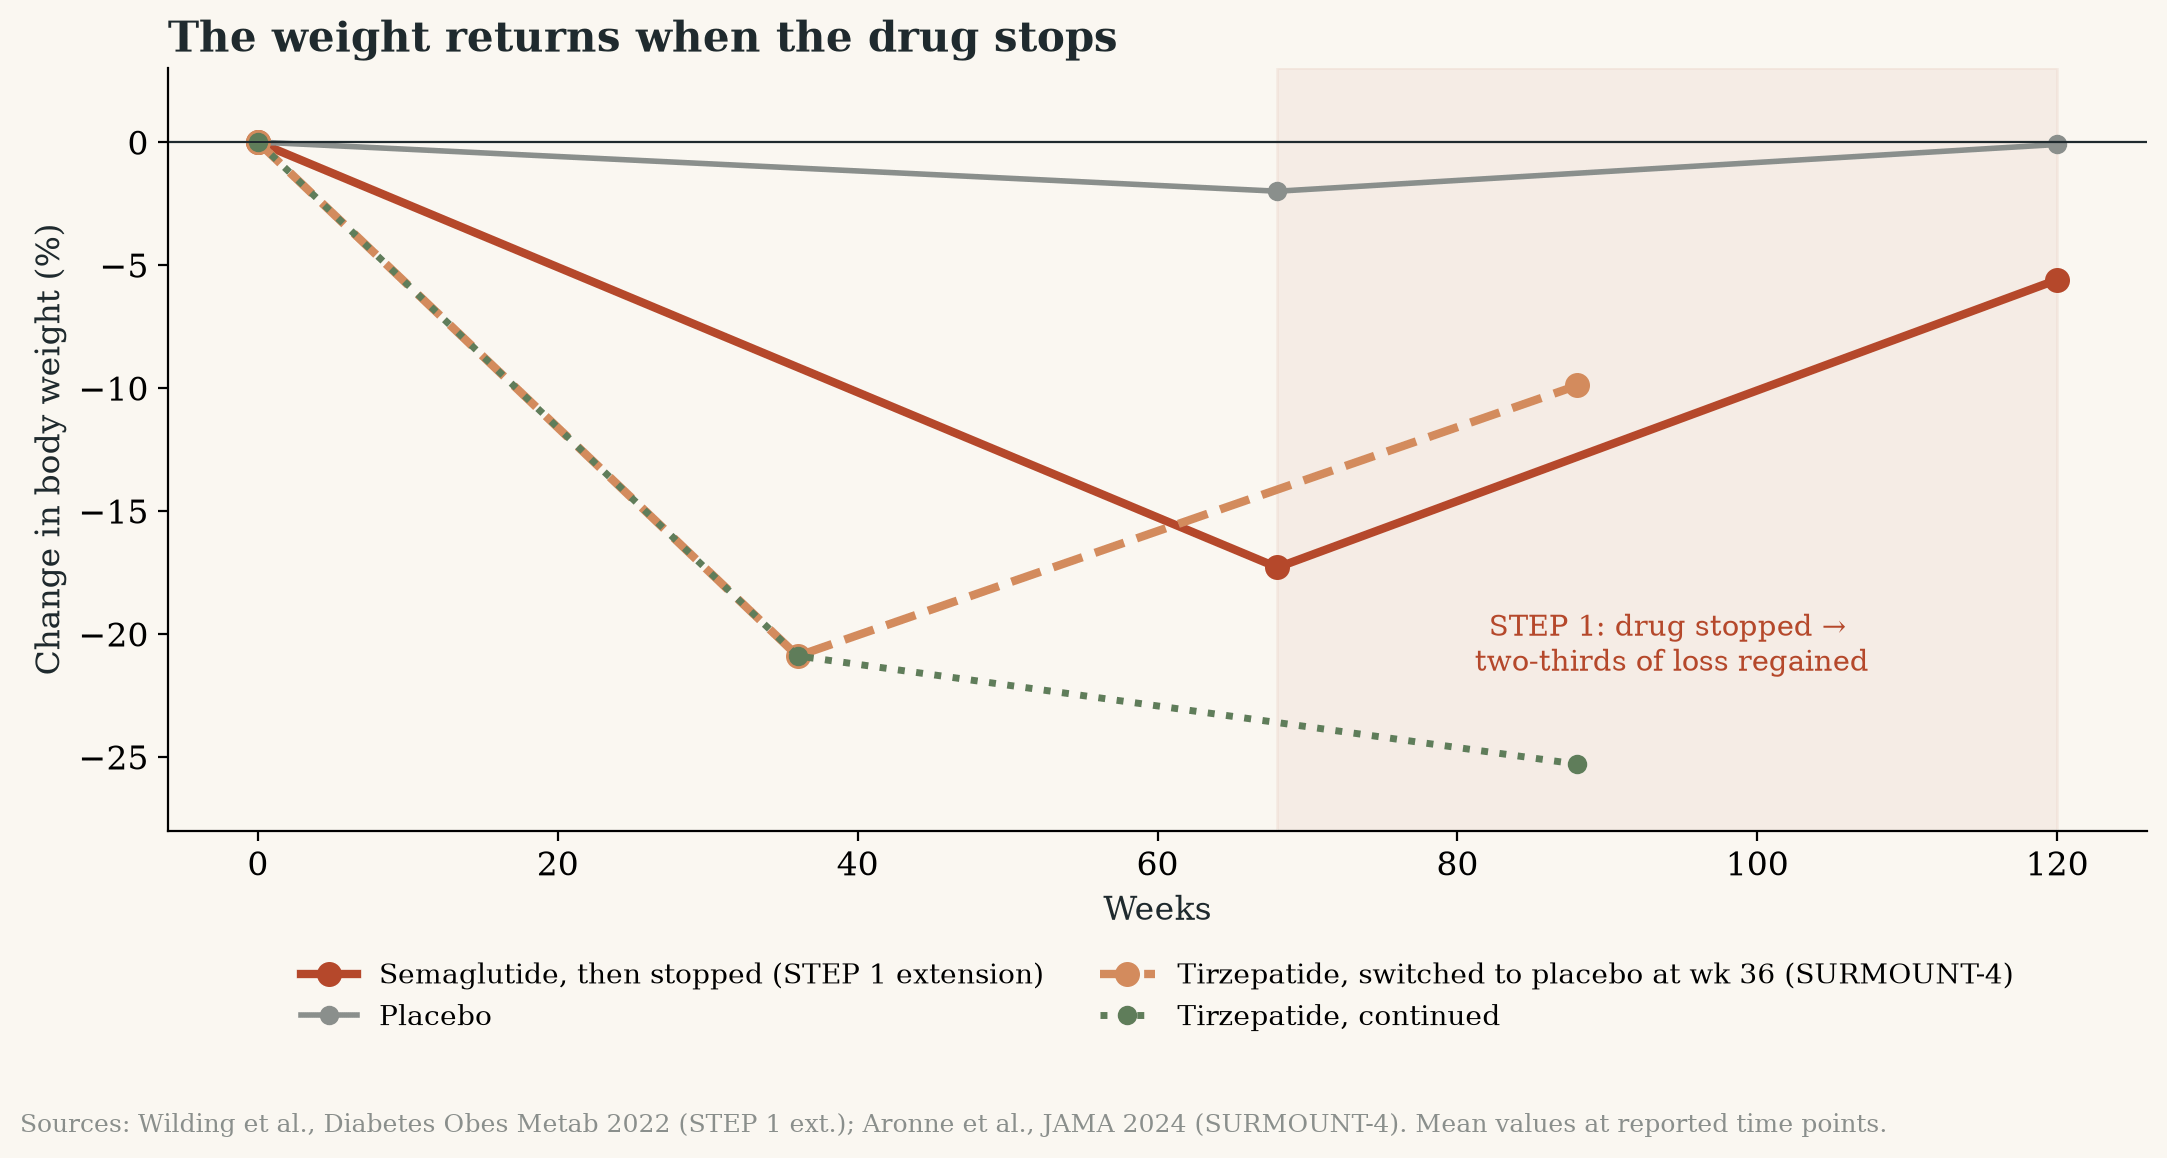
The industry’s response to this is revealing. Rather than conclude that the drug isn’t addressing the cause, it has redefined obesity as a chronic, relapsing disease that needs lifelong medication (WHO guideline, JAMA, 2026). The failure to cure has been rebranded as proof of chronicity.
And in the real world, most people don’t stay on the drug anyway. In a Danish national registry study of 77,310 adults starting Wegovy for weight loss, 52% stopped within a year (Medscape, reporting EASD 2025). So the predictable trajectory for millions of people is this: lose weight, including muscle, stop the drug, regain weight, mostly as fat, and end up with a worse body composition than when they started.
Exhibit B: You Are Losing More Than Fat
That last point deserves its own section, because it goes directly to my concern with regeneration and resilience.
In the STEP 1 body-composition substudy, roughly 40% of the weight people lost on semaglutide was lean mass (European Heart Journal, 2026). Lean mass includes skeletal muscle, the largest site of glucose disposal in the body and one of our strongest predictors of healthy aging.
Think about what that means. A drug sold to correct a metabolic disorder strips away a large share of the very tissue that best protects metabolic health. Then, when the drug is stopped and the weight returns, it does not come back as muscle.
The contrast with a root-cause approach is instructive. In a randomized NEJM trial of weight-loss maintenance, only the strategy that combined exercise with the drug improved insulin sensitivity, glycated hemoglobin, and cardiorespiratory fitness. The drug alone did not (Lundgren et al., NEJM, 2021). Movement, one of the ancestral inputs I emphasize throughout REGENERATE, carried the real metabolic benefit.
Exhibit C: A Hormone Signal the Body Never Evolved to Receive
This is the part of the story that most clearly separates the regenerative view from the pharmaceutical one.
Your body already makes GLP-1. Specialized L-cells in the gut lining release it after you eat. One of the most elegant ways your body triggers its own GLP-1 is through the short-chain fatty acids your gut bacteria produce when they ferment fiber from whole plant foods. Cambridge researchers showed that these microbial metabolites directly stimulate GLP-1 secretion from L-cells through a dedicated receptor called FFAR2 (Tolhurst et al., Diabetes, 2012).
This is what I mean when I write, in REGENERATE, that “food is not just an energy source but information and software for your body.” When you eat fermentable fiber from real plants, your microbiome translates it into a hormonal message that tells your body it has been fed. The system was designed to work this way.
Now compare the natural signal with the drug:
The evidence: native GLP-1 vs. semaglutide
Native GLP-1 has a half-life of about 2 minutes. It is rapidly broken down by the enzyme DPP-4 and cleared by the kidneys (Diabetes, Obesity and Metabolism review).
Semaglutide was chemically modified to resist that breakdown. Its half-life is about one week, roughly 165 hours (RCSB PDB-101), and it stays in circulation for about five weeks after the last dose (StatPearls).
The comparison: the drug’s signal lasts roughly 5,000 times longer than the body’s own (165 hours ÷ 2 minutes).
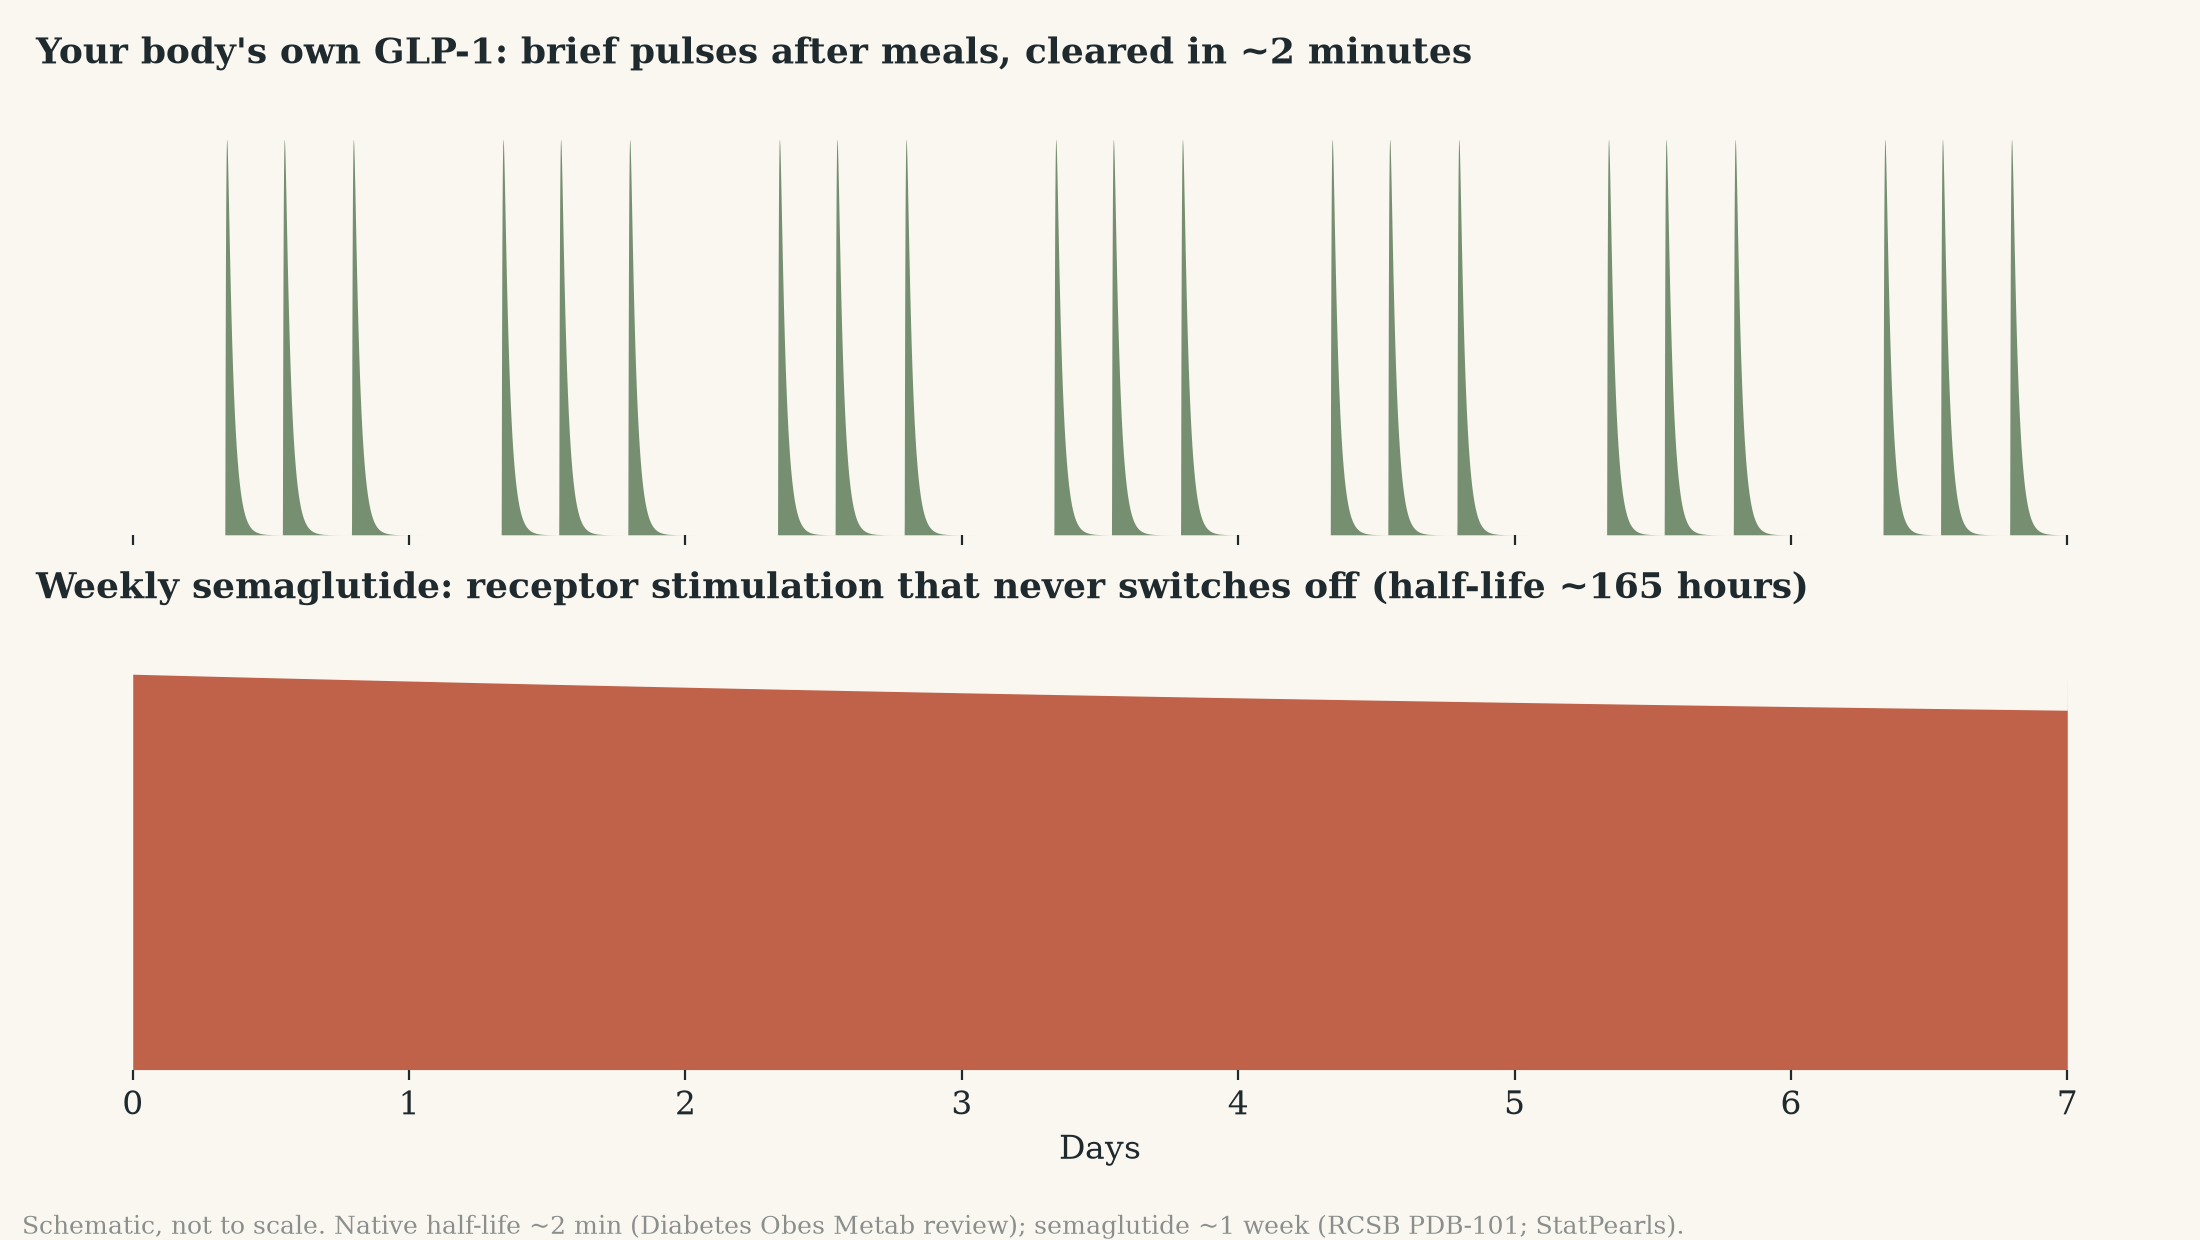
Your body evolved to release GLP-1 in brief pulses tied to meals and then clear it within minutes. Semaglutide keeps the receptor switched on around the clock, week after week, for years. That is not “mimicking a natural hormone,” as the marketing says. It is replacing a finely timed conversation with a single, continuous, deafening tone.
When you look at the side effects in that light, they are not mysterious. A gut held in a state of permanent, pharmacologically enforced slowdown is a gut at risk of the very injuries now documented in the literature.
Exhibit D: The Risk Side of the Ledger
I recently completed a separate, fully sourced audit of GLP-1 safety evidence. Here are the highlights relevant to a risk-benefit judgment. I keep established harms separate from contested ones, because the case is stronger when it doesn’t overreach.
Pancreatitis, bowel obstruction, gastroparesis (Established): Compared with another weight-loss drug, GLP-1 users had about 9 times the pancreatitis risk, 4.2 times the bowel-obstruction risk, and 3.7 times the gastroparesis risk (Sodhi et al., JAMA, 2023)
Severe and fatal pancreatitis (Established): The UK regulator strengthened warnings after 1,296 reports, 19 of them fatal and 24 necrotizing (MHRA, January 2026)
Gallbladder disease (Established): 37% higher risk overall, more than doubled at weight-loss doses, across 76 trials (He et al., JAMA Internal Medicine, 2022)
Optic nerve stroke (NAION) (Established outside the U.S.): Europe’s regulator classified it as a very rare side effect of semaglutide, at about twice the baseline risk (EMA, 2025); the U.S. label still does not list it (regulatory ledger)
Kidney, arthritic, and blood-pressure effects (Probable): Increased interstitial nephritis, kidney stones, arthritic disorders, hypotension, and fainting in more than 2 million veterans (Xie & Al-Aly, Nature Medicine, 2025)
Thyroid cancer and suicidality (Contested): French data showed a signal (Bezin et al., Diabetes Care, 2023); the largest independent studies did not (Pasternak et al., BMJ, 2024; FDA, 2026)
On the benefit side, the strongest case is the SELECT trial in people who already had cardiovascular disease. Major cardiovascular events occurred in 6.5% of the semaglutide group versus 8.0% of the placebo group over about 40 months (Lincoff et al., NEJM, 2023). That is a 20% relative reduction, and it is a real benefit for a high-risk group.
The math behind the headline
Absolute difference: 1.5 percentage points over more than three years.
Number needed to treat: roughly 67 people (1 ÷ 0.015) for about three years to prevent one event.
Who it applies to: a population that already had heart disease. It does not establish benefit for the general overweight population now being prescribed these drugs.
Funding: the trial was funded by Novo Nordisk.
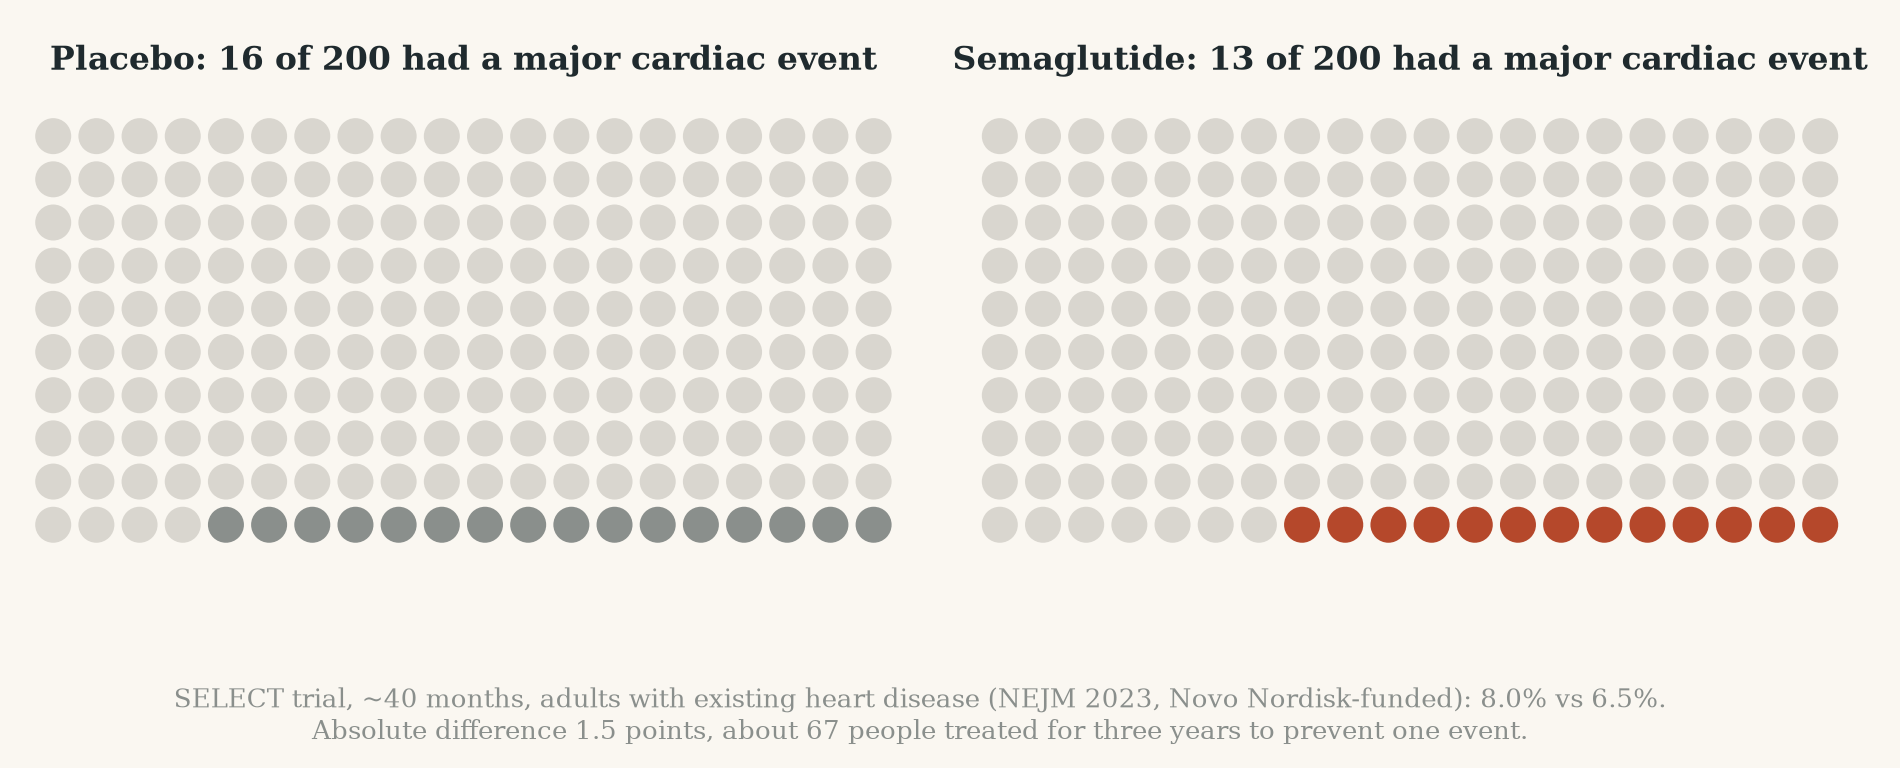
Now set that modest absolute benefit next to the harms above, the near-certain weight regain on stopping, the loss of muscle, and a commitment to a drug for life. The risk-benefit calculation for a 35-year-old with a few extra pounds and no heart disease looks very different from the one in SELECT.
Exhibit E: What the Root Cause Actually Looks Like
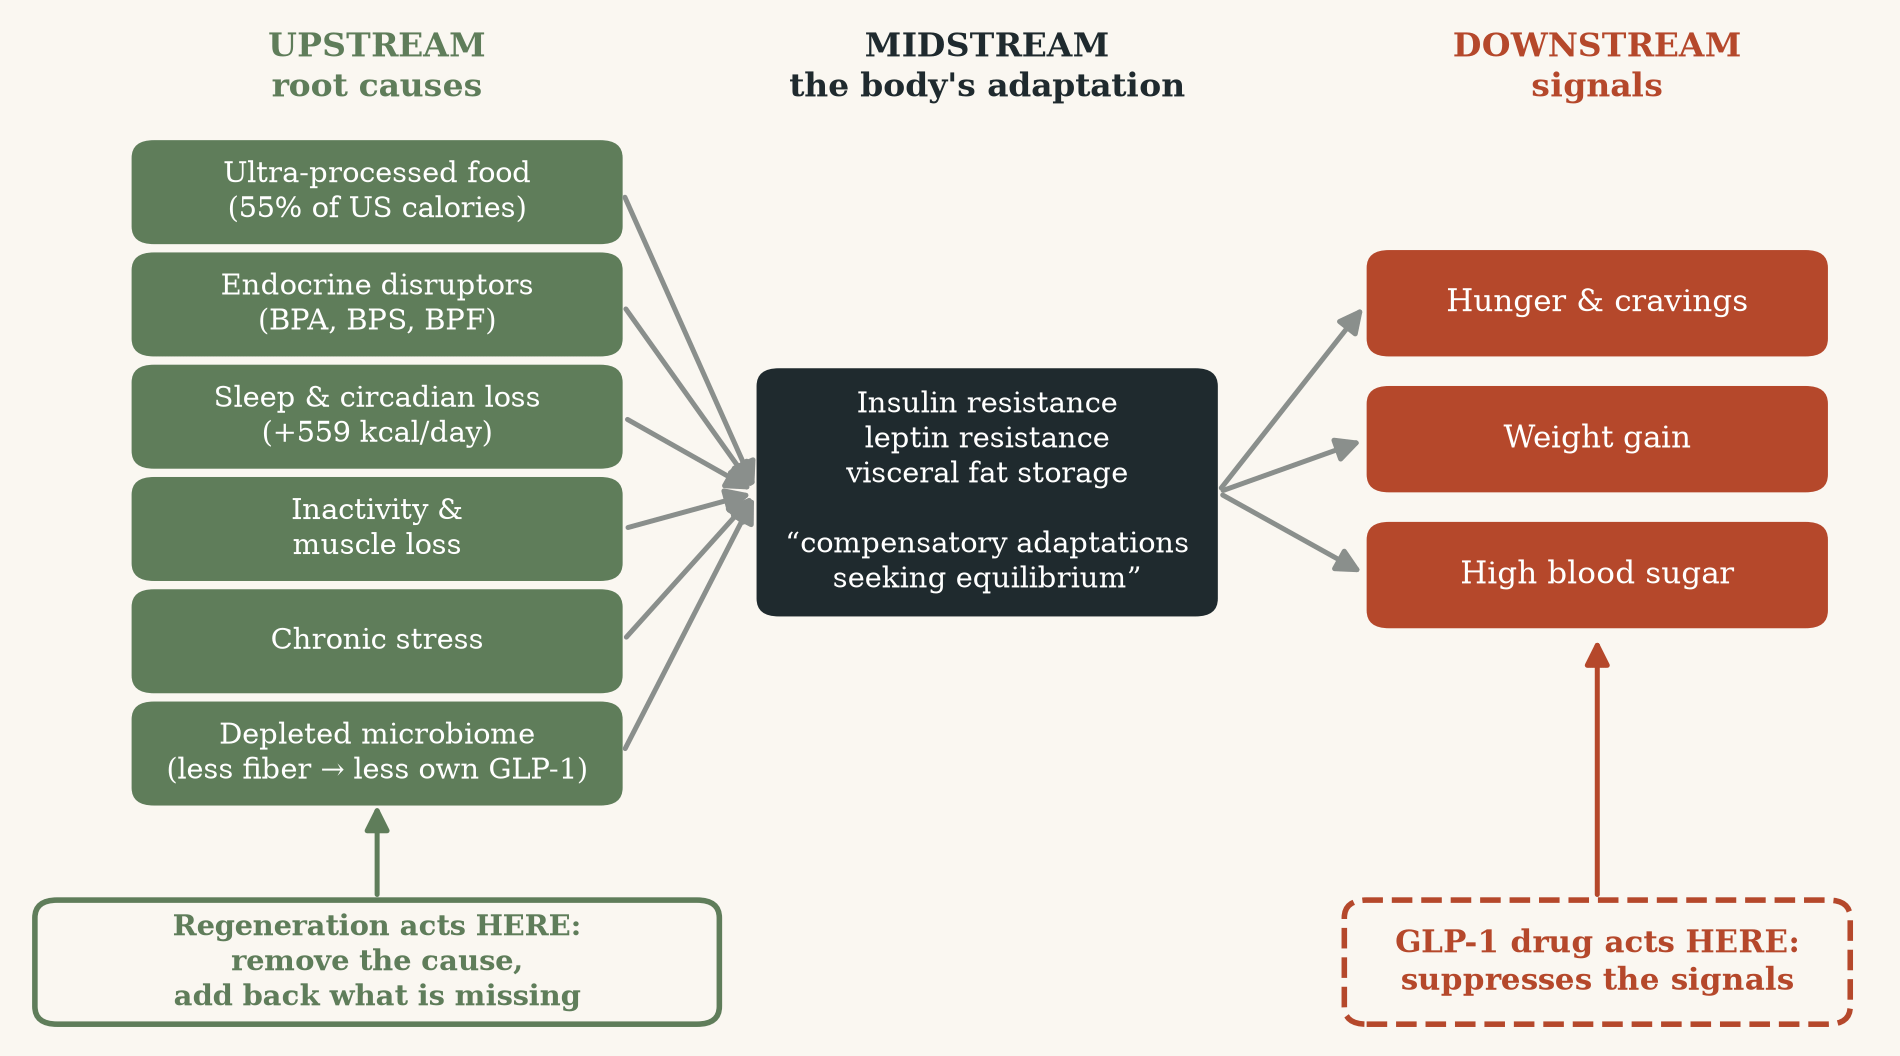
If the drug addresses the downstream signal, what is upstream? The evidence points to a set of inputs that are well documented and largely ignored in the prescription-first model.
Ultra-processed food
Americans now get 55% of their calories from ultra-processed foods. For children and teenagers it is 61.9% (CDC NCHS Data Brief 536, 2025).

That is not a minor detail. In a tightly controlled NIH inpatient trial, the same people ate about 508 more calories per day on an ultra-processed diet than on an unprocessed one. The two diets were matched for presented calories, sugar, fat, fiber, and sodium, and the participants gained weight on one and lost it on the other (Hall et al., Cell Metabolism, 2019).
In other words, the food itself overrides satiety. This is exactly what I described in REGENERATE about industrial ingredients engineered to hijack our “biologically hard-wired taste receptors.”
Endocrine-disrupting chemicals
The Endocrine Society’s second scientific statement lists “obesity and diabetes” among the areas with “strong mechanistic, experimental, animal, and epidemiological evidence for endocrine disruption” by environmental chemicals (Endocrine Reviews, 2015). In REGENERATE I discuss bisphenols in particular: the BPA in can liners and receipts, and the BPS and BPF quietly substituted for it in “BPA-free” products.
No injectable drug removes those chemicals from your body or your pantry.
Sleep and circadian disruption
In a randomized trial, cutting sleep to two-thirds of normal for eight nights increased calorie intake by 559 calories per day, with no change in energy expenditure (Calvin et al., Chest, 2013). A drug that suppresses appetite does nothing for the sleep deprivation that drove it.
Lifestyle versus drug, head to head
The landmark Diabetes Prevention Program randomized more than 3,000 high-risk adults. Intensive lifestyle change cut progression to diabetes by 58%; metformin cut it by 31% (DPP Research Group, The Lancet, 2009).
In the DiRECT trial, a structured diet program delivered in ordinary UK primary care put 46% of participants with type 2 diabetes into remission at 12 months, off all diabetes drugs, compared with 4% of controls. Among those who lost 15 kg or more, 86% achieved remission (Lean et al., The Lancet, 2017).
I should be honest about the hard part. At five years, sustained remission in DiRECT had fallen to about 13% in the group that stayed in the program, though 40% were still off diabetes medication (Lancet Diabetes & Endocrinology, 2024). Lifestyle change is hard to sustain when you go back into the same environment of ultra-processed food, chronic stress, poor sleep, and chemical exposure.
But notice what that finding actually proves. It does not show that the root-cause approach fails. It shows that the root cause is environmental and still active, and that an individual’s willpower alone cannot overcome an entire food system. That is an argument for changing the environment, not for medicating people for life so they can keep living in it.
Exhibit F: The Absurdity, Fully Assembled
Put the pieces together and the picture becomes almost satirical.
The food industry creates the problem. It feeds Americans a diet that is 55% ultra-processed. Controlled trials show this kind of diet makes people overeat by hundreds of calories a day.
The pharmaceutical industry sells the fix. Lilly and Novo Nordisk spent more than $270 million on payments to more than a quarter-million U.S. prescribers from 2018 to 2025 (The Washington Post, via ADN). The FDA formally warned Novo Nordisk that a televised special promoting its drugs was “false or misleading” and minimized their risks (FDA Warning Letter, 2025).
The food industry sells products for the people on the fix. Nestlé, Conagra, and others now sell “GLP-1 Friendly” products. One such frozen pizza delivers 40% of the daily value for sodium and saturated fat. Smoothie King’s “GLP-1” smoothie has more calories than a Krispy Kreme glazed doughnut. The USDA confirmed that there is “no regulatory standard” for the term “GLP-1 Friendly” (Associated Press, 2026).
The cycle extends to children. Children get about 62% of their calories from ultra-processed foods, and the American Academy of Pediatrics now advises pediatricians to offer weight-loss drugs to adolescents 12 and older. A BMJ analysis found financial ties to GLP-1 makers “throughout” the guideline process (Schmidt et al., The BMJ, 2025).
There is a cycle here, and every turn of it is profitable. Sick people are a recurring revenue stream. People who get well are not.
What Regeneration Asks of Us Instead
The core of my philosophy, laid out in REGENERATE, is simple enough to fit in a single sentence:
“On the most basic level, regeneration constitutes removing what the body does not need, and adding back what it does.”

Applied to metabolic disease, that means a different set of priorities than a weekly injection:
Remove what does not belong. Cut ultra-processed foods, industrial fructose and high-fructose corn syrup, and flavor-manipulating additives like MSG. Reduce bisphenols and other endocrine disruptors by avoiding canned foods, plastic containers, and thermal-paper receipts.
Add back what was lost. Eat whole, fiber-rich plant foods and resistant starches that feed the microbes that make your body’s own GLP-1. Get real sunlight, protect your sleep, and move with intensity. Short bursts of high-intensity interval training can rapidly improve glucose metabolism in people with insulin resistance.
Respect the signal. Hunger, cravings, insulin resistance, and the accumulation of belly fat are not defects to be overridden. They are, as I write in the book, “compensatory adaptations seeking to re-establish equilibrium.” They tell you that something in your environment is wrong.
People with severe, established disease who need a medication should have access to it. The point is not to shame anyone for taking a drug or to deny that some high-risk patients may benefit. The point is that a society that responds to an epidemic driven by food, chemicals, sleep loss, and stress by putting one in eight adults on a lifelong appetite-suppressing injection has decided not to ask the most important question.
In REGENERATE I wrote that “it’s hardly news that more than two-thirds of Americans are overweight” and that metabolic syndrome is “an optimal example of a chronic disease category that can be universally mitigated and reversed through diet, lifestyle choices,” and through addressing the maladaptive stress response. I stand by that. The science of the last decade has only strengthened it.
The fire is still burning. The alarm is doing its job. The question is whether we will keep paying to silence it.
For more research on thousands of natural approaches to overweight and obesity, consult the extensive databases on the topic on GreenMedInfo.com.


This article is for educational purposes and is not medical advice. Do not stop or change any prescribed medication without consulting a licensed healthcare professional, particularly if you have diabetes or cardiovascular disease.
In my teens and married life i fought the Battle of the Bulge for years. It was impossible to lose weight, because i knew nothing about nutrition. Today, I weigh 105- 107 pounds without using any kind of drugs, because i learned how to eat as human beings were designed to eat...natural foods. The moment, I would eat a slice of bread, i gained weight. I gave up all grains in 1986, when i got arthritis..I learned over time that by eliminating many of the touted 'good' foods - my health improved. I am healthier and more active at 92 than I was at 30. Natural unprocessed food that does not come with a label is the only way to live a longer and healthier life.. This is what mankind lived on for eons of time.
If one had to identify one major cause of insulin resistance and heart disease it would be the big lie that fat, not sugar is the primary cause.
(cut and paste)
Timeline and Rise
• Late 1940s–1950s: Researchers published early studies connecting high-fat diets with elevated blood cholesterol and cardiovascular risks.
• 1960s: Health organizations and physicians began recommending low-fat eating patterns to the general public.
• Late 1970s–1980s: Formal government guidelines (such as early U.S. dietary goals) institutionalized the push to slash total and saturated fat. (Much of this was based on a study by a researcher named Ancel Keys, of 22 countries that showed a low fat diet was healthier than one that included a moderate amount of fat; the problem was he excluded 15 countries that didn't fit his theory).
• 1990s "Low-Fat Craze": The ideology peaked as manufacturers flooded grocery stores with "low-fat" or "fat-free" processed foods (like SnackWell's cookies), often replacing removed fat with added sugars and refined carbohydrates to preserve taste.
• The Paradox:
Despite widespread adherence to low-fat guidance during the 1980s and 1990s, national rates of obesity and type 2 diabetes climbed sharply. Critics and public health researchers later noted that replacing fats with refined carbohydrates and extra calories contributed to the unintended rise in weight gain.
• Consensus Shift: Major health institutions, including the Harvard T.H. Chan School of Public Health, later characterized the rigid low-fat/high-carb push as a flawed public health experiment, leading to a modern emphasis on healthy, whole-food fats rather than strict fat-elimination.
What's missing from this information is it was done purposely by the sugar industry. IOW, we were had.